 GPAtlas
GOUT
gpatlas.co.uk
🔍 When to Suspect
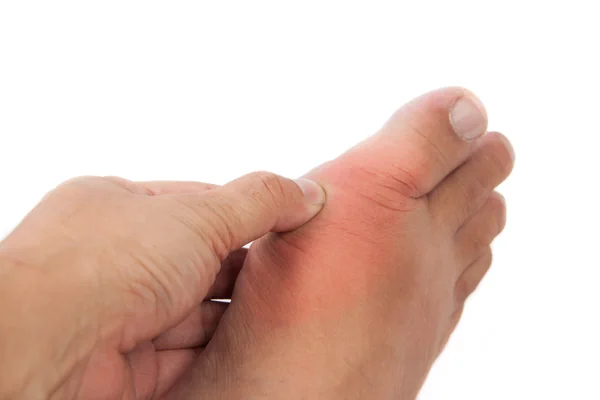
Sudden onset of severe pain, redness, warmth, and swelling in a single joint, most commonly the first metatarsophalangeal (MTP) joint (big toe), especially with risk factors like diet, alcohol, or diuretic use
🩺 Assessment
- ◉ Symptoms + triggers → Sudden, severe, fluctuating joint pain with redness, swelling, and warmth
- ◉ Risk factors/history → Personal/family history, diet high in purines (red meat, seafood), alcohol (especially beer), obesity, CKD, diuretic use
- ◉ Impact + mimics → Affects ability to walk or wear shoes; key mimic is septic arthritis
- ◉ Exam findings → Erythema, swelling, warmth, and exquisite tenderness of affected joint; check for tophi (on ears, fingers, elbows) in chronic gout
💊 Management
🔸Key tests:
➤ Serum uric acid (if normal during a flare, recheck at least 2 weeks after it settles; treatment target <360 µmol/L), U&Es/eGFR to assess renal function
🔸Lifestyle:
➤ Reduce intake of purine-rich foods and sugary drinks; avoid alcohol during flares; advise weight management and hydration; during a flare: rest, elevate, and use ice packs
🔸Pharmacological:
➤ Acute Flare:
➤ 1st line: High-dose NSAID (e.g. naproxen), consider PPI cover, OR Colchicine 500mcg 2-4 times daily (max 6mg per course)
➤ Also 1st line: Short course of oral corticosteroid (e.g. prednisolone 30–35mg once daily for 3–5 days)
➤ Continue existing urate-lowering therapy (ULT) throughout a flare
➤ Long-Term (ULT): Offer for multiple or troublesome flares, tophi, chronic gouty arthritis, CKD stages 3–5 or diuretic therapy; discuss with anyone else after a flare. Start at least 2–4 weeks after a flare settles (or during a flare if flares are frequent)
➤ 1st line: Allopurinol, start 100mg daily (50mg in CKD 4/5), titrate up every 4 weeks to target urate <360 µmol/L (consider <300 µmol/L with tophi, chronic gouty arthritis or ongoing frequent flares)
➤ 1st line alternative: Febuxostat 80mg daily – equal first-line choice to allopurinol (NICE NG219); MHRA: use with caution in major CVD (allopurinol preferred)
➤ Prophylaxis: Discuss flare prevention when starting or titrating ULT; if wanted, offer colchicine 500mcg once or twice daily while the target urate is being reached (low-dose NSAID or oral corticosteroid if colchicine is unsuitable)
🔸Exacerbation/emergency:
➤ Urgent hospital admission if septic arthritis is suspected
🔸Follow-up/safety-net:
➤ When starting allopurinol, warn about rare but serious risk of Allopurinol Hypersensitivity Syndrome (rash, fever)
⚠️ Red Flags
• Suspicion of septic arthritis → Fever, systemically unwell, unable to bear weight or actively move the joint
• Severe, uncontrolled pain despite initial treatment
➡️ Referral Criteria
Urgent: Immediate hospital admission if septic arthritis is suspected
Routine: Refer to Rheumatology for diagnostic uncertainty, contraindications to standard treatment, CKD stages 3b–5 (eGFR <45) or organ transplant, or uncontrolled symptoms
📌 GP Tips
🔹Serum uric acid level can be falsely normal during an acute flare-up
🔹Always rule out septic arthritis in a single hot, swollen, painful joint